

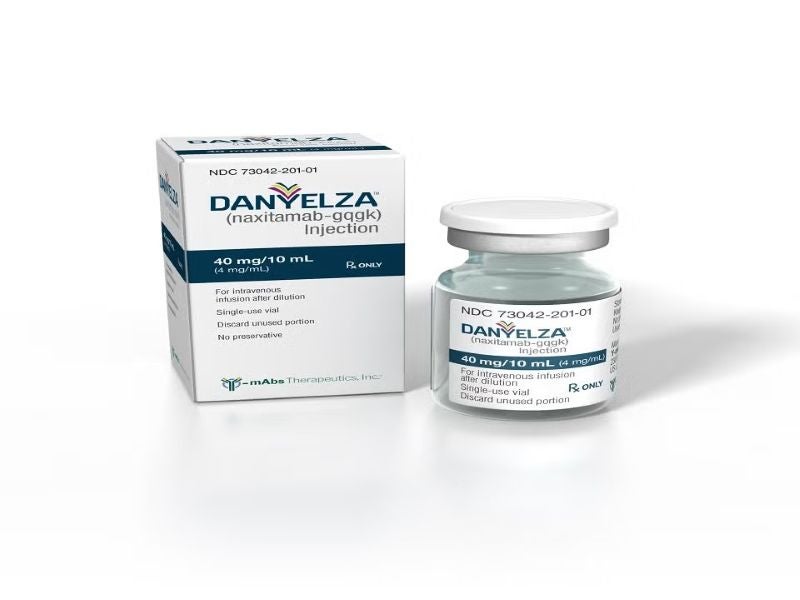

Danyelza® (naxitamab-gqgk) is a humanised immunotherapy indicated in combination with granulocyte-macrophage colony-stimulating factor (GM-CSF) for the treatment of high-risk neuroblastoma (HR-NB).
The drug is eligible to treat paediatric patients aged one year and older and adult patients with relapsed or refractory high-risk bone or bone marrow neuroblastoma that achieved a partial or mild response, or stable pre-treatment disease.
Recommended Buyers Guides

Danyelza was developed by Y-mAbs Therapeutics, which was acquired by SERB Pharmaceuticals in September 2025. It is available as a 40mg/10ml (4mg/ml) clear to slightly opalescent and colourless to slightly yellow solution in a single-dose vial for intravenous administration.
Danyelza approvals
Researchers at Memorial Sloan Kettering Cancer Center (MSK) developed Danyelza, which is exclusively licensed to Y-mAbs Therapeutics for development and manufacturing.
Y-mAbs submitted the biologics licence application for naxitamab to the US Food and Drug Administration (FDA) under the FDA’s Rolling Review process in March 2020, which was accepted for priority review in June 2020.
The drug holds orphan drug, breakthrough therapy and rare paediatric disease designations from the FDA.
In November 2020, the FDA approved Danyelza (naxitamab) in combination with GM-CSF for the treatment of HR-NB in adult and paediatric patients (older than one year).
The drug was approved by the Israeli Ministry of Health in August 2022, followed by China’s National Medical Products Administration in December 2022. It was also approved by the Brazilian Health Regulatory Agency in May 2023.
Y-mAbs Therapeutics reached an agreement with the European Medicines Agency and its Pediatric Committee on a Pediatric Investigation Plan (PIP) for naxitamab in February 2023. The PIP details how the product will be tested in children. European regulatory authorities require an approved PIP before a company can file a Marketing Authorisation Application.
In May 2025, the drug was recommended by the National Comprehensive Cancer Network® (NCCN) Clinical Practice Guidelines in Oncology (NCCN Guidelines®) as a NCCN Category 2A treatment option for high-risk neuroblastoma.
Neuroblastoma causes and symptoms
Neuroblastoma is a rare form of solid tumour that typically arises in very early nerve cells outside the brain, before birth.
This form of cancer begins in the sympathetic nervous system, which is responsible for regulating involuntary body processes such as breathing, heart rate and digestion, leading to tumours in the abdomen as well as in the spine, chest, neck or pelvis.
The clinical behaviour of neuroblastoma is extremely variable, with some tumours being easy to treat, while others can be very aggressive.
Children with neuroblastoma are graded into risk categories depending on their chances of recovery. Low-risk children can often be cured with a small strategy, whereas high-risk children require more comprehensive care to increase their survival chances.
All patients are staged based on the International Neuroblastoma Staging System Committee system, from stage one through stage 4S.
Patients with stage four cancers diagnosed after one year of age are listed as high-risk, where tumour neuroblastoma cells have already metastasised to other locations in the body such as the bone or bone marrow.
Treatment for neuroblastomas relies on whether the condition is low-risk or high-risk and whether it is the first incidence of relapse.
The symptoms include a lump or swelling in the abdomen, neck, legs, upper chest or face; enlarged belly; breathing or swallowing problems; weight loss; not eating or feeling full; problems with bowel movements or urinating; pain in bones; blue lumps or bumps in the skin; drooping eyelid and small pupil (the black area in the centre of the eye) in one eye; problems being able to feel or move parts of the body; and bulging or bruising around the eyes.
Naxitamab’s mechanism of action
Naxitamab-gqgk is the first and only FDA-approved humanised monoclonal antibody that targets the glycolipid GD2.
GD2 is a disialoganglioside highly expressed in various neuroectoderm-derived tumours and sarcomas as well as neuroblastoma cells.
Naxitamab binds to GD2 on the cell surface in vitro and triggers complement-dependent cytotoxicity and antibody-dependent cell-mediated cytotoxicity.
Clinical trials on Danyelza
FDA approval of Danyelza in combination with GM-CSF was evaluated in two open-label, single-arm clinical studies named Study 201 (NCT 403363373) and Study 12-230 (NCT 01757626).
The efficacy was assessed in a subpopulation of patients with HR-NB with refractory or relapsed bone or bone marrow disease and who showed a partial response, minor response or stable disease to prior therapy. The trial excluded patients with progressive disease.
In both trials, patients underwent at least one systemic treatment before enrolment to treat conditions outside of the bone or bone marrow.
Patients received a 9mg/kg/cycle of Danyelza in three separate intravenous infusions of 3mg/kg on days 1, 3 and 5 of each cycle. On days 1–5, GM-CSF was administered at 250 micrograms (µg)/m2/day at days -4–0 and at 500µg/m2/day at days 1–5 subcutaneously.
The primary efficacy outcomes in both the trials were overall response rate (ORR) and duration of response.
In Study 201, 22 patients were included in the efficacy analysis receiving Danyelza with GM-CSF. The patients achieved an ORR of 45% with 36% complete responses. The median duration of response in the patients was 6.2 months.
In Study 12-230, 38 patients were included in the efficacy analysis receiving Danyelza with GM-CSF. The patients showed an ORR of 34% with a 26% complete response rate. Approximately 23% responded with a duration of response of more than six months.
The frequent side effects that occurred in more than 50% of the patients receiving Danyelza were pain, diarrhoea, cough, infusion-related reactions and vomiting, as well as decreased appetite, nausea and fast heartbeats.
